Getting a pimple—well, something that looks like a pimple—on your finger can feel weird. Sure, it might look like a whitehead, blackhead, or deep acne bump, but actual acne is pretty rare on fingers. Most of the time, that bump is something else entirely: a blister, wart, cyst, insect bite, eczema flare-up, or a mild skin infection.

Where the bump is really matters. Your palms and fingertips don’t have hair follicles, which are usually where acne pops up. So if you spot a pimple-like bump on your palm, a clear bubble on your fingertip, or a group of itchy bumps between your fingers, chances are it’s not acne.

This guide is here to help break down what finger bumps might mean, what you can do at home (without making things worse), and when it’s time to check in with a doctor. Whether you’ve got a tiny white bump on your fingertip or a painful lump oozing pus, we’ve got some answers.

Is it Really a Pimple?

Honestly, it’s probably not. True pimples (acne) happen when oil, dead skin, and inflammation clog up a hair follicle. Fingers don’t have many of those. Palms and fingertips? They don’t have any.

Finger bumps that look like pimples are usually something else, like:

– Friction blisters
– Dyshidrotic eczema
– Contact dermatitis
– Warts
– Bacterial infection
– Infected hair follicle
– Herpetic whitlow
– Digital mucous cyst
– Ganglion cyst
– Insect bites
– Callus or corn
– Reaction to a splinter or something stuck under the skin

Don’t freak out—Google tends to turn small bumps into medical dramas. Most finger bumps aren’t dangerous. Still, don’t squeeze anything you haven’t identified. That can make a mild infection way worse.

What Does Your Finger Bump Actually Look Like?

What you see and feel gives clues, but it’s not a sure diagnosis. Check this quick chart:

What You Notice Possible Explanations
Tiny, clear, very itchy bubbles Dyshidrotic eczema, contact dermatitis
One clear bubble after rubbing or pressure Friction blister
Painful group of clear blisters Herpetic whitlow
White/yellow center with heat, redness Bacterial infection, abscess
Rough bump with dark dots Wart
Smooth bump near last finger joint/nail Digital mucous cyst
Firm lump near joint or tendon Ganglion cyst, other deep lump
Hard white bump Callus, wart, tiny cyst, calcium deposit
Tender bump after splinter/puncture Foreign body reaction or infection
Itchy bumps between fingers Eczema, contact dermatitis, scabies
Red, swollen skin around nail Paronychia
Deep, throbbing fingertip pain Fingertip infection (felon)

Lots of skin problems look alike. Don’t jump straight to acne products—they might make the situation worse.

Common Causes of Pimple on Fingers

1. Friction Blister

Blisters pop up when repeated rubbing causes skin layers to separate—fluid fills the gap. Anything from tools and sports gear to gardening, gaming, tight rings, or odd pressure can cause one.

Looks like:
– Smooth, clear bubble
– Tender raised spot
– Blood-filled if tiny blood vessels broke
– Usually exactly where you got rubbed

Wondering why you’ve got a clear bubble? Think about what you did with your hands in the last day or two. New workout, marathon cleaning, hand tools, tight jewelry—they’re all possible triggers.

Don’t pop a blister. Wash gently, cover it, and avoid whatever caused the rubbing. If it bursts, leave the skin unless it’s really dirty or has fully detached.

2. Dyshidrotic Eczema

This form of eczema causes little clusters of tiny, deep blisters—super itchy. Usually on the sides of fingers, fingertips, or palms. People call these “tapioca bubbles.”

Triggers:
– Stress
– Sweating/hot weather
– Repeated handwashing
– Metals (nickel, cobalt)
– Cleaning products

This might explain bumps on fingertips, little whiteheads on the palm, or bumps on the side of your index finger. Later, the blisters dry, crack, or peel.

Stress makes eczema worse, so if your thumb breaks out after a rough week, it’s probably eczema—not “stress pimples.”

Use a thick (fragrance-free) moisturizer after washing. Avoid harsh soaps, and try wearing cotton-lined gloves for wet chores. If it gets really bad, a doctor might prescribe a steroid cream.

3. Contact Dermatitis

If something touches your skin that it doesn’t like, you get redness, itching, tiny blisters, cracked skin, maybe swelling or bumps between fingers. Hands encounter it all—soaps, sanitizers, gloves, fragrances, cleaning sprays, metals, hair products.

If you’re breaking out between fingers and on your face, recall if both areas touched the same thing—like a new nail product or hair dye. Or it might just be coincidence.

4. Common Wart

Warts on fingers or knuckles feel rough, grainy, and can have little black dots (tiny blood vessels). People sometimes mistake these for blackheads, but real blackheads are rare here.

Warts spread through touch or shared items, especially if skin’s already broken. Don’t pick, bite, or shave warts. Salicylic acid wart treatments work on the common kind—but don’t use them if the bump is unknown, inflamed, infected, or bleeding. People with diabetes, poor circulation, or numb fingers should check with a doctor first.

5. Bacterial Folliculitis (Infected Hair Follicle)

Hair does grow on backs of fingers and knuckles. Shaving, plucking, or small cuts can inflame the follicle—closest thing to a true finger pimple.

May look like:
– Red bump at a hair
– Small whitehead
– Tender spot
– Sometimes pus

Don’t squeeze! Try a warm (not hot) compress for 10–15 minutes a few times a day and keep it clean. If it spreads or gets more painful, see a doctor.

6. Boil or Skin Abscess

A boil is a painful lump filled with pus—a deeper infection. Might start as a tiny, sore bump that looks like a pimple, but then gets redder, warmer, and hurts more.

Large, pus-filled bumps deserve caution. Sometimes a doctor has to drain an abscess. Never try to pop it at home—could make things worse.

Hand infections can be risky since swelling can interfere with tendons, joints, nerves, and movement.

7. Paronychia

This is infection around the nail—often after biting nails, picking at cuticles, or too many manicures.

Symptoms:
– Redness along nail edge
– Swelling
– Tenderness
– Pus beside or under the nail
– Throbbing pain

Warm-water soaks help mild cases, but worsening pain or pus pocket needs medical treatment. Don’t poke with needles.

8. Herpetic Whitlow

Herpes simplex virus can infect a finger, producing severe pain, swelling, tingling, and clusters of blisters—clear or cloudy. Can mimic blisters, pimples, or bacterial infections.

Exposure usually comes from contact with another herpes blister or your own cold sore.

Don’t drain these blisters—the fluid can spread the virus. Cover it, keep it away from others, and see a doctor. Antiviral meds work best early. NHS suggests keeping it clean and covered, and avoiding contact with others and your own eyes until it heals.

9. Digital Mucous Cyst

A smooth, shiny bump near your nail or fingertip joint. May have clear, jelly-like stuff inside, sometimes creates a groove in the nail.

Usually:
– Smooth bump near pinkie or joint
– Pimple–like, but not really
– Firm, clear lump that returns or doesn’t go away

Common in older adults, sometimes linked to joint wear. Don’t poke it—risking joint infection isn’t worth it. A doctor should check any cyst that’s painful, leaking, or just won’t go away.

10. Ganglion Cyst

Noncancerous, fluid-filled lump related to a joint or tendon. Usually near the wrist, but fingers get them too.

Feels like:
– Firm bead under skin
– Changes size
– Hurts when moving the joint
– Sometimes described as a tiny bead at finger base
– Deeper pimple-like feel

This isn’t acne. Don’t try old home remedies like smashing it with a book (seriously, people do this)—you’ll just hurt your hand. Sometimes it resolves, other times needs doctor help.

11. Callus or Corn

A “callous pimple” is probably just thickened skin from repetitive pressure. Writers, musicians, gym goers, hand-tool users get them often.

Usually:
– Hard, not fluid-filled
– Grows slowly
– Over pressure point
– Has regular skin lines
– Hurts when pressed or rubbed

Ease up on the cause and moisturize. Don’t cut it. If it has dark dots, disrupts normal skin lines, grows, or doesn’t go away—it could be a wart or something else.

12. Insect Bite or Sting

Bites give red, itchy, sometimes pus-like bumps—fire ant stings are famous for small, sterile pustules.

Watch for:
– Sudden appearance after outdoor time
– Multiple bumps
– Strong itching
– Central puncture mark
– Other bites nearby

Cool compress and avoid scratching. Get help if you get trouble breathing, throat/tongue swelling, dizziness, or hives.

13. Splinter or Foreign-Body Reaction

A tiny piece of wood, metal, glass, thorn, or plant can get stuck. Your skin forms a tender bump around it. Sometimes you can spot a dark line or dot, sometimes not.

Don’t dig deep. Shallow splinters should come out with clean tweezers, but deeper, painful ones need a professional. Check that your tetanus shot is current after a puncture.

14. Scabies

Scabies causes really itchy bumps, often between fingers, wrists, elsewhere. Itching usually worse at night. If others in your household itch too—it’s a clue.

This isn’t about hygiene. Acne products won’t help; you need scabies-specific treatment.

15. Rare Causes

Persistent finger lumps can come from arthritis, benign tumors, calcium deposits, inflammatory problems, or very rarely, skin cancer. Don’t assume—it mostly won’t be cancer. But if a bump keeps growing, bleeding, changing color, hurting the nail, or just won’t heal, get it checked.

What About Color?

Color gives hints—but not a definite answer.

White bump?

– Could be a tiny eczema blister, friction blister, pustule, thickened skin, wart, cyst, or calcium deposit.

White doesn’t always mean pus; sometimes clear fluid under thick skin looks white.

Red bump?

– Could be inflammation, bite, dermatitis, folliculitis, or infection. If it’s hot, swelling, throbbing, or spreading—watch out for infection.

Black dots?

– Warts, tiny scabs, splinter, dried blood, or pigment. Since real blackheads don’t show up on fingers, don’t use extractor tools.

Green, blue, or purple?

– A green bruise with finger bump probably means healing bruise. Bruises change color as they heal. Green discharge, though, is a warning for infection. If your finger goes numb, cold, painful, or won’t move, check in with a doctor.

Should You Worry About a Painful Whitehead on Your Finger?

A small, painful white bump on your fingertip isn’t usually just acne. Fingertip tissue is tightly packed—if infection or swelling builds up, it gets really uncomfortable.

Call a healthcare provider ASAP if you notice:

  1. Deep, throbbing fingertip pain
  2. Tense, swollen fingertip pad
  3. Pus
  4. Growing warmth/redness
  5. Pain after a puncture, splinter, bite, or cut
  6. Trouble bending the finger
  7. Red streaks moving up your hand/arm
  8. Fever or feeling really sick

Deep fingertip infections often need antibiotics or draining—don’t wait it out.

Safe Home Care for a Finger Bump

When the bump is small and doesn’t have warning signs, simple care beats crazy treatments.

Do:

  • Gentle washing with lukewarm water, mild soap
  • Remove rings before finger swells
  • Cool compress for itchy bites/rash
  • Warm compress for minor inflamed hair follicle
  • Fragrance-free hand cream for dry skin/eczema
  • Cover open skin with a clean dressing
  • Take pictures daily to track changes
  • Note triggers (tools, gloves, chemicals, products)

Don’t:

  • Pop, cut, burn, or poke the bump
  • Use wart remover unless it’s definitely a wart
  • Put acne products (benzoyl peroxide, acids) on cracked/blistered skin
  • Apply bleach, essential oils, toothpaste, or household cleaners
  • Use leftover antibiotics
  • Share nail tools
  • Keep wearing a ring on a swelling finger

Hands take a beating—too much treatment often makes a tiny bump way worse.

When to See a Doctor

Get medical care if the bump:

  • Has pus or keeps draining
  • Gets increasingly painful
  • Feels hot or has spreading redness
  • Lasts more than 1–2 weeks
  • Returns again and again
  • Grows fast
  • Bleeds for no reason
  • Causes nail damage
  • Limits finger movement
  • Came after an animal/human bite or deep puncture
  • Happens in someone with diabetes, poor circulation, weak immune system

Urgent care if:

  • Red streaks rise up your arm/hand
  • Fever, chills, or you feel really sick
  • Finger turns pale, blue, cold, or numb
  • Severe swelling or ring is stuck
  • You can’t bend/straighten finger
  • Pain is intense, deep, or getting worse fast
  • Fingertip is tight/throbbing
  • You get a painful cluster of blisters (herpetic whitlow warning)

Wounds on hands can let infections spread. Keeping things clean and covered lowers the risk.

How Doctors Figure Out What’s Going On

They’ll ask:
– When did it start?
– Does it itch, burn, throb, or hurt when pressed?
– Did you have a cut, splinter, bite, manicure, or new exposure?
– Did you see fluid, blood, or pus?
– Are there other bumps elsewhere?
– Any history of eczema, arthritis, diabetes, herpes, or circulation problems?
– Anyone else in your house itching or rashy?

They might use a magnifier, take swabs, do a scraping, order an X-ray or ultrasound, or sample tissue—but usually, they just need to look and ask.

Most finger bumps don’t need fancy tests—or drama. Just some smart attention.

You can’t always stop finger bumps from popping up, but a few habits make them less likely:

– Moisturize after washing your hands.
– Go for fragrance-free soap when you can.
– Wear gloves if you’re dealing with wet work or chemicals.
– Let sweaty gloves dry out before using them again.
– Don’t swap towels, razors, or nail tools with anyone.
– Don’t chew your nails or pick at your cuticles.
– Clean and cover small cuts right away.
– Take splinters out safely—don’t just dig at them.
– Use padded grips or gloves if you’re working with tools over and over.
– Try not to touch cold sores or open wounds.
– Skip shaving or plucking hair on your fingers unless there’s a good reason.

Clean hands are good, but scrubbing with harsh soap until your skin’s raw isn’t helpful. That only messes up your skin barrier and leaves you open to irritation or infection.

Frequently asked questions

Q. Can you get acne on your hands?
Actual acne on hands isn’t common—the skin there doesn’t have as many oil glands as your face, chest, or back. Your palms and fingertips don’t even have hair follicles, so typical acne can’t really form. If you see “pimples” on your hands, it’s probably a different kind of bump.

Q. Why do I get tiny pimples between my fingers?
Tiny bumps between your fingers can show up if you have eczema, contact dermatitis, scabies, irritation, or tiny blisters. If the bumps itch a lot at night, spread, or everyone in the house is scratching, it could be scabies—see a doctor for that.

Q. What about a hard white bump on a finger?
A hard white bump could be anything from a wart or callus to a small cyst, a reaction to something stuck in your skin, or a calcium deposit. If it hurts, gets bigger, or won’t go away, let a doctor take a look.

Q. Why does the bump hurt?
If the bump on your finger hurts, it might be inflamed or infected, pressing on a nerve, sitting right over a joint, or constantly rubbing on something. If it’s throbbing, hot, swollen, has pus, or you can’t move your finger normally, get it checked out.

Q. Is a pimple under the finger skin actually a cyst?
It’s possible. But it could also be a ganglion, a reaction to something under the skin, a deep infection, or something going on with your joint. Either way, don’t try to pop or drain it yourself.

Q. What’s a smooth, pimple-like bump on the pinkie?
It might be a blister, mucous cyst, ganglion cyst, or another harmless lump. Where it sits—right by the nail, over a joint, near a tendon, or a spot that gets a lot of pressure—gives clues.

Q. What causes little bumps on the knuckles?
They could be warts, calluses, irritated hair follicles, eczema, bug bites, or small lumps from joints. If you see “blackheads” on your knuckles, they’re more likely wart dots, old scabs, or random stuff stuck in the skin—not real blackheads.

Q. What if a small clear bump sticks around?
A small, clear bump that won’t go away could be a recurring eczema blister or mucous cyst. If it’s near your nail or a joint and just keeps coming back, let a doctor take a look. And don’t poke or pop it.

Q. How do I treat an infected pimple on my finger?
Don’t squeeze it. Wash the area, keep it covered, and if it’s got pus, is growing, getting hotter, or really hurts, get some medical advice. Deeper infections sometimes need antibiotics or help from a professional.

The bottom line

A bump or “pimple” on your finger usually isn’t true acne. Clear or itchy bumps are often eczema or just irritation. Rough bumps with dark spots are usually warts. Smooth lumps near a joint can be cysts. Hot, painful bumps with pus spell infection.

Until you know what it is, keep the area clean, protect it from rubbing, and don’t try to pop it—save that energy for your stress ball. Go see a doctor if you notice bad pain, pus, spreading redness, fever, trouble moving your finger, lots of painful blisters, or a bump that just won’t heal.


By Kulmeet Kundlas MD, Board-Certified Internal Medicine — Shield Medical Group, Sebring and Lake Wales, Florida. Schedule Urgent Care.

If you are over 50 and living with type 2 diabetes, you have heard the noise about the GLP-1 drugs. On August 28, 2026, the FDA changed the label for Mounjaro (tirzepatide), and it is worth your attention. The agency now says this medication does more than lower your A1C, help your blood pressure, and ease sleep apnea. It also lowers your risk of a future heart attack and stroke.

Most of us in primary care already suspected this. What changed on August 28 is that it is now official, printed on the package, and something I can tell you with confidence in the exam room. Let me explain what the studies actually found and where this drug fits for you.

Watch Dr. Kundlas explain the FDA’s Mounjaro heart-protection approval and what it means for you:

Is Mounjaro Just a Cosmetic Weight-Loss Drug?

No. For a long time tirzepatide was used only for two jobs: bringing down A1C and taking off weight. As of August 28, the FDA has added a third, and it is the one that matters most for longevity — reducing the risk of heart attack and stroke.

For you, that means when we start this medication we are not just chasing better lab numbers. There is a real, measured layer of protection for your heart that comes with it.

What the SURPASS Cardiovascular Trial Showed


The study was set up in an honest way. We already had Trulicity (dulaglutide), a GLP-1 drug proven to cut the risk of heart attack and stroke. So the researchers did not test Mounjaro against a placebo. They tested it head-to-head against Trulicity.

It was a big trial: about 13,000 patients in more than 30 countries. And these were not lightly treated people. Their blood pressure medication, their cholesterol medication, their diet, their exercise, and their Trulicity were all maximized before Mounjaro entered the picture. Even against that bar, Mounjaro held its own and then edged slightly ahead on cardiovascular events.

The gap was about one percentage point. That sounds like nothing until you remember how many people take these drugs. Across a population, one point is a very large number of strokes and heart attacks that did not happen.

Why Would a Diabetes Drug Protect Your Heart?

Diabetes is an inflammatory disease, not just a sugar problem. I tell patients to picture high blood sugar as liquid sandpaper, quietly scraping the inside lining of the blood vessels day after day. That irritation drives the inflammation that leads to heart attacks and strokes.

Mounjaro works on two receptors at once, GLP-1 and GIP. That dual action seems to calm the inflammation more than a single-receptor drug, and in the trial that showed up as fewer cardiovascular events. It is not a guess. The researchers measured inflammatory markers, not just weight and glucose.

This is the direction all of diabetes care is moving, away from “get the A1C down” and toward “fix the metabolic disease.” The American Diabetes Association Standards of Care reflect that shift, and it is the same reason we now reach for SGLT2 inhibitors, which protect the kidneys and the heart and help keep patients out of heart failure.

Side Effects and Who Should Not Take It

None of this is free. The stomach and bowel side effects are what limit the drug for most people:

  • Nausea is the common one, worst when you start or step up the dose, and it usually settles over a few weeks.
  • Diarrhea or constipation happens in a smaller number of people and is generally mild.
  • Pancreatitis is rare but real. Severe abdominal pain that will not let up needs to be checked right away.
  • Medullary thyroid cancer or MEN 2 syndrome in you or your family is a reason not to use this class at all.

Outside of those situations, most people do well on it.

The Lifestyle Factor


Here is what worries me. I am watching people start one of these medications and then quietly ease off the walking, the lifting, and the cooking. When a pill starts doing the work, it is human nature to stop doing yours. Every physician I know has this same fear.

Remember how the heart benefit was found: in people who had already maxed out their treatment and their habits. The drug added to that. It did not replace it. If you skip your part, I do not think you get the full result. On any GLP-1 medication you need to:

  • Do resistance exercise, so you keep the muscle you would otherwise lose along with the fat.
  • Eat enough protein to protect that muscle.
  • Stay active every day. A short walk after your biggest meal still helps your sugar and your heart.

You cannot take a molecule this strong and change nothing else.

The Bigger Picture

I believe these drugs get closer to the root of the problem than anything we have had. Trial after trial has shown the same thing: help a person with diabetes lose weight, and heart disease, stroke, liver disease, and overall mortality all move in the right direction. Mounjaro’s makers had to prove that to regulators before they could print it on the box. They did. For those of us treating patients, it is a confirmation of something we already believed.

Newer medicine keeps arriving. Our job is to stay healthy enough to take advantage of it when it does, and to keep holding up our end in the meantime.

Frequently Asked Questions

Does the FDA approval mean Mounjaro is now a heart medication?

It means Mounjaro is approved to reduce the risk of heart attack and stroke in adults with type 2 diabetes who have cardiovascular disease or risk factors, on top of its diabetes and weight uses. It does not replace your blood pressure, cholesterol, or blood-thinning medications.

How is Mounjaro different from Ozempic or Trulicity?

Trulicity (dulaglutide) and Ozempic (semaglutide) act on one receptor, GLP-1. Mounjaro (tirzepatide) acts on two, GLP-1 and GIP. That tends to produce more weight loss, and in the SURPASS cardiovascular trial it gave at least as much heart protection as Trulicity.

Will I still get the heart benefit if I don’t exercise or change my diet?

Probably not all of it. Everyone in the trial had already maximized diet, exercise, and their other medications. The heart protection was measured on top of that base, not instead of it.

Who should not take Mounjaro?

Anyone with a personal or family history of medullary thyroid cancer or MEN 2 syndrome. People with a history of pancreatitis should weigh it carefully with their doctor. Stop the medication if you are planning a pregnancy or become pregnant.

What are the most common side effects?

Nausea, especially early on or after a dose increase. Diarrhea and constipation are less common. Pancreatitis is rare.

The Bottom Line

If you are on Mounjaro, this is good news you can trust: it now has evidence behind it for protecting your heart, not only your blood sugar and your weight — as long as you keep doing the lifestyle work alongside it. Ask your primary care physician whether it fits your plan. If you do not have one, here is why that matters.

At Shield Medical Group in Sebring and Lake Wales, Florida, we manage GLP-1 therapy and heart risk together every day. To be seen, call (863) 236-9550 or book a same-day appointment.

Educational only; talk to your clinician about your own situation. This is Dr. Kundlas — like, share, and subscribe, and I will see you in the next video.

By Kulmeet Kundlas MD, Board-Certified Internal Medicine — Shield Medical Group, Sebring and Lake Wales, Florida. Schedule Urgent Care.

Over the past year, more women have come into my office with the same surprised look and the same story: “Doctor, I wasn’t trying to get pregnant — I was just trying to lose weight on Ozempic.” The internet has given this a nickname, “Ozempic babies,” and it has traveled faster than the science behind it. So let me walk you through what we actually know, what we don’t, and what you need to do if you are on a GLP-1 medication and there is any chance of pregnancy.

The short version: these medications are not fertility drugs. But in the right person, they can quietly remove the roadblocks that were preventing ovulation in the first place — and that can lead to an unexpected pregnancy.


A GLP-1 injectable pen beside a positive pregnancy test on a clinic tray, illustrating the Ozempic babies trend.
Watch Dr. Kundlas explain the “Ozempic babies” trend, fertility, and the contraception warning: 

The Ozempic Baby Trend — What It Actually Describes

We have noticed a real pattern: spontaneous, unexpected pregnancies in younger women with obesity who are being treated with GLP-1 receptor agonists such as semaglutide (Ozempic, Wegovy) and tirzepatide (Mounjaro, Zepbound). Why it happens is almost certainly multifactorial, and I want to be careful here — based on the studies and the physiology we understand today, we cannot say these are anti-infertility medications.

What we can say is that they appear to correct several underlying mechanisms that block conception in the first place: insulin resistance, irregular or absent ovulation, and the hormonal disruption of polycystic ovary syndrome (PCOS).

Why Weight Loss Helps Fertility

It is a well-established fact that insulin resistance drives anovulatory cycles — menstrual cycles in which you do not release an egg. High circulating insulin pushes the ovaries to make more androgens, disrupts the normal FSH and LH signals from the brain, and the follicle never matures or releases.

When you lose weight, insulin resistance falls. Cycles become more regular. Ovulation returns. And once you are ovulating predictably again, the chance of pregnancy goes up — sometimes in the very first cycles, before a woman even realizes her body has “switched back on.”

GLP-1 Effects on Ovulation


A physician in a white coat talking with a woman patient in a bright exam room about GLP-1 medication and pregnancy planning.

Obesity and insulin resistance impair ovulation. GLP-1 receptor agonists improve metabolic dysfunction, help normalize menstrual irregularities, and can restore ovulation — particularly in women with obesity and PCOS. Reports have clearly shown increased spontaneous and unexpected pregnancies in women treated with semaglutide.

The key question is why. Is it a direct drug effect on the ovary, or is it simply the weight loss and the improved insulin sensitivity that come with it? Right now the evidence points mostly to the second explanation — the medication is removing a metabolic obstacle, not acting as a fertility treatment.

Mounjaro’s Birth Control Warning — This Part Is Concrete

There is one place where the science is not fuzzy at all. The current FDA prescribing information for tirzepatide — sold as Mounjaro and Zepbound — states that it can reduce the effectiveness of oral hormonal contraceptives. This is due to delayed gastric emptying, which changes how the pill is absorbed, and the effect is largest when you first start and after each dose increase.

The FDA labeling advises women using oral birth control to either switch to a non-oral method (such as an IUD or implant) or add a barrier method for 4 weeks after starting tirzepatide and for 4 weeks after every dose increase. Mounjaro, Zepbound, and tirzepatide are the same molecule — the warning applies to all of them.

Semaglutide (Ozempic, Wegovy) does not carry this same oral-contraceptive warning in its label, but I still recommend the same precautions. If pregnancy would be a problem for you, do not rely on the pill alone while you are on any GLP-1.

What the Studies Actually Show

Do we truly know pregnancies are increasing on these drugs? Increasingly, yes — in the observational literature. In 2024, published data described a rise in unexpected, spontaneous pregnancies among women treated with GLP-1 agonists.

But be careful about how you read this. One analysis of 1,936 women with a documented diagnosis of infertility treated with semaglutide or tirzepatide did not demonstrate that these medications improve infertility. The women lost significant weight, and it could not be separated out whether any benefit was a direct “Ozempic effect” or simply the result of the weight loss itself. That distinction matters — it is the difference between a fertility drug and a metabolic drug with a fertility side effect.

Pregnancy Safety Guidance

What about fetal safety? So far, in the available observational studies, we have not seen a clear teratogenic signal — no confirmed increase in birth defects among pregnancies exposed to GLP-1 agonists. But that data is still limited, and “no signal yet” is not the same as “proven safe.”

Because of this, the guidance across the board is that pregnancy on these medications should be planned. If you intend to conceive, stop the GLP-1 at least two months beforehand. Semaglutide in particular has a long half-life, which is why the two-month washout window exists.

The Bottom Line and Your Next Steps

“Ozempic babies” have a biologically plausible basis, but the story gets overstated online. I do not want anyone walking away thinking these are infertility medications — they are not. What we believe today is that weight loss lowers insulin resistance, insulin resistance falling restores ovulation, and restored ovulation can lead to pregnancy.

So, practically:

  • Assume your fertility may return within weeks of starting a GLP-1, especially if you have PCOS or irregular cycles.
  • Use reliable contraception — a non-oral method, or the pill plus a barrier method, particularly in the first 4 weeks and after every dose increase on tirzepatide.
  • Plan pregnancy deliberately. Stop the medication at least two months before trying to conceive.
  • If you become pregnant or think you might be, tell your doctor immediately so the medication can be stopped and your prenatal care started.

The observational evidence is clear enough: your chance of getting pregnant goes up on these medications. Talk to your primary care physician, get the right precautions in place, and do not be caught by surprise. If you don’t have a primary care doctor, this article explains why that gap matters.

At Shield Medical Group in Sebring and Lake Wales, Florida, we manage GLP-1 therapy every day and talk through exactly these issues — contraception, pregnancy planning, and safe weight loss. To be seen, call (863) 236-9550 or book a same-day appointment.

Frequently Asked Questions

Do Ozempic and Mounjaro make you more fertile?

Not directly. They are not fertility drugs. In women with obesity or PCOS, the weight loss and improved insulin sensitivity they produce can restore normal ovulation, which increases the chance of pregnancy. The effect is a downstream result of metabolic improvement, not a direct fertility treatment.

Can I get pregnant on Ozempic even with an IUD?

An IUD is one of the most effective methods available and is not affected by delayed gastric emptying the way the oral pill is. No method is 100%, but an IUD or implant is a good choice while you are on a GLP-1.

Why does Mounjaro affect birth control pills but Ozempic doesn’t?

The FDA label for tirzepatide (Mounjaro, Zepbound) specifically documents reduced absorption of oral contraceptives from slowed stomach emptying, mainly when starting and after dose increases. Semaglutide’s label does not carry that specific warning, but similar caution is reasonable.

How long should I stop a GLP-1 before trying to conceive?

At least two months. Semaglutide has a long half-life, so a washout period lets the drug clear before pregnancy.

I just found out I’m pregnant and I’m on Ozempic. What do I do?

Contact your doctor right away. The usual step is to stop the medication and begin prenatal care. Current observational data has not shown a clear increase in birth defects, but the medication is not recommended during pregnancy.

The Bottom Line

These medications can restore a fertility you thought was gone — quietly, and sometimes quickly. Respect that. Use real contraception, plan any pregnancy on purpose, and keep your doctor in the loop.

Educational only; talk to your clinician about your individual situation. This is Dr. Kundlas — I’ll see you in the next one.

By Kulmeet Kundlas MD, Board-Certified Internal Medicine — Shield Medical Group, Sebring and Lake Wales, Florida

Your blood pressure, cholesterol, and hemoglobin A1C are not just numbers on a lab report. A single result is a snapshot. Repeated measurements over time can tell the story of your health and help identify problems before they become harder to treat.

I am Dr. Kulmeet Kundlas, a primary care physician with more than 30 years of experience. In my clinic, men often ask the same practical questions: “What should my blood pressure be?” “What does my A1C mean?” “Should I worry about my cholesterol?” This guide explains the vital men’s health numbers and preventive screenings that deserve your attention.

Educational only; talk to your clinician.

Why Your Health Numbers Matter

One abnormal blood pressure reading, cholesterol level, or blood sugar result does not always establish a diagnosis. Measurements can be affected by sleep, stress, illness, medications, exercise, alcohol, caffeine, and how the test was performed.

What matters is the pattern. When we track your numbers across annual visits, lab work, and home monitoring, we can see whether a risk is improving, stable, or moving in the wrong direction. That gives you and your clinician time to act before a preventable problem becomes a heart attack, stroke, kidney disease, or type 2 diabetes.

Schedule Your Annual Physical Near Your Birthday

A simple habit can make preventive care easier: schedule your annual physical around your birthday. Many people naturally reflect on their goals around that time of year. Pairing your birthday with an annual health visit creates a practical reminder to review your medications, vaccines, screening tests, labs, sleep, exercise, and mental health.

Your needs are personal. Your family history, smoking history, medications, weight, medical conditions, race and ethnicity, and prior test results may change which screenings make sense and when to begin them.

How USPSTF Recommendations Work

The U.S. Preventive Services Task Force, usually called the USPSTF, is an independent panel that reviews evidence for preventive services. Its letter grades do not mean that a test is automatically right or wrong for every individual. They summarize the balance of likely benefit and likely harm for the population addressed by the recommendation.

USPSTF Grade What It Generally Means
A High certainty that the preventive service has substantial net benefit.
B High certainty of moderate benefit, or moderate certainty of moderate to substantial benefit.
C Offer selectively based on the patient’s circumstances, preferences, and clinical judgment. The overall benefit is small for the population addressed.
D Discourage use because the service has no net benefit or the harms outweigh the benefits.
I Statement Current evidence is insufficient to determine whether benefits outweigh harms.

These recommendations evolve as new evidence becomes available. That is why preventive care should be reviewed regularly instead of relying on an old checklist.

The Vital Numbers Every Man Should Know

1. Blood Pressure

Blood pressure is one of the most important health numbers because uncontrolled high blood pressure increases the risk of stroke, heart attack, heart failure, kidney disease, and other complications. The USPSTF recommends screening adults age 18 and older with an office blood pressure measurement, with measurement outside the clinic used to confirm a diagnosis before treatment begins when appropriate.

For many adults, a blood pressure goal below 130/80 mm Hg is commonly used, but the right target depends on your age, health conditions, medications, and risk of treatment side effects. Do not diagnose yourself from one high reading.

  • Normal: Less than 120/80 mm Hg.
  • Elevated: Systolic 120–129 mm Hg and diastolic below 80 mm Hg.
  • Stage 1 hypertension: Systolic 130–139 mm Hg or diastolic 80–89 mm Hg.
  • Stage 2 hypertension: Systolic at least 140 mm Hg or diastolic at least 90 mm Hg.

For a reliable home reading, sit quietly for at least five minutes, keep both feet flat on the floor, support your arm at heart level, use the correct cuff size on the upper arm, and avoid caffeine, smoking, or exercise for 30 minutes beforehand. A validated upper-arm monitor is generally preferred over a wrist monitor.

Urgent note: A reading of 180/120 mm Hg or higher can be serious. If it is accompanied by chest pain, shortness of breath, weakness, numbness, trouble speaking, severe headache, vision changes, or confusion, call 911. If you have a very high reading without symptoms, contact a clinician promptly for guidance.

2. Body Mass Index and Waist Size

Body mass index, or BMI, uses height and weight to estimate whether weight may be affecting health risk. It is useful as a screening tool, but it does not directly measure body fat and can be misleading in some people with high muscle mass or certain body types.

  • 18.5–24.9: Standard BMI range.
  • 25.0–29.9: Overweight range.
  • 30.0 or higher: Obesity range.

For many men, waist circumference adds useful information because abdominal fat is strongly associated with insulin resistance, type 2 diabetes, fatty liver disease, sleep apnea, and cardiovascular disease. A waist measurement above 40 inches in men is associated with increased cardiometabolic risk, although ethnicity and individual health factors matter.

3. Blood Sugar and Hemoglobin A1C

Your hemoglobin A1C estimates your average blood sugar over roughly the prior two to three months. A fasting glucose is a point-in-time measurement. Both can be useful, especially when a pattern is developing.

Test Typical Prediabetes Range Typical Diabetes Threshold
Hemoglobin A1C 5.7% to 6.4% 6.5% or higher, usually confirmed with repeat testing unless symptoms and marked high glucose are present
Fasting glucose 100 to 125 mg/dL 126 mg/dL or higher, usually confirmed with repeat testing
Two-hour oral glucose tolerance test 140 to 199 mg/dL 200 mg/dL or higher, usually confirmed with repeat testing

The USPSTF recommends screening for prediabetes and type 2 diabetes in adults ages 35 to 70 who have overweight or obesity. Earlier testing may be appropriate when a person has risk factors such as family history, high blood pressure, abnormal cholesterol, sleep apnea, a history of cardiovascular disease, or symptoms of high blood sugar.

If you have prediabetes, it is not a reason to panic. It is a chance to intervene. Weight loss when indicated, regular physical activity, improved sleep, more fiber and protein-rich foods, and fewer sugary beverages can reduce the risk of progression to type 2 diabetes.

4. Cholesterol and Cardiovascular Risk

Cholesterol results are important, but no single cholesterol number tells the whole story. Your clinician considers LDL cholesterol, HDL cholesterol, triglycerides, blood pressure, smoking status, diabetes status, family history, age, and other factors to estimate your overall risk of heart attack and stroke.

Think of cardiovascular risk as a long-term accumulation. High blood sugar can injure blood vessel lining. High blood pressure adds mechanical stress. LDL cholesterol can contribute to plaque formation in the damaged vessel wall. When these problems occur together, risk rises.

Ask for a conversation about your full cardiovascular risk rather than focusing only on whether your total cholesterol is “good” or “bad.” For some men, lifestyle changes are enough. For others, medications such as statins meaningfully reduce risk.

5. Depression, Alcohol, Tobacco, and Drug Use

Preventive care is not limited to lab values. Depression screening is important because depression is common, treatable, and often missed in men who may describe irritability, poor sleep, fatigue, alcohol overuse, withdrawal from family, or loss of motivation instead of sadness.

Tobacco use should be addressed at every visit. Quitting can take several attempts, and needing more than one attempt does not mean you have failed. Medication, nicotine replacement, counseling, and structured support improve the chance of success.

Alcohol and substance-use screening also matter. Be honest with your primary care team. The goal is not judgment. It is identifying risks early and helping you protect your health, relationships, work, and safety.

Cancer Screenings Men Should Discuss

Colorectal Cancer Screening

For adults at average risk, the USPSTF recommends colorectal cancer screening from age 45 through age 75. Several effective options exist, including stool-based tests and visual exams such as colonoscopy. The best test is often the one you are willing and able to complete on schedule.

Adults ages 76 to 85 may benefit selectively based on overall health, previous screening history, and preferences. Screening is generally not recommended after age 85.

Lung Cancer Screening

Annual low-dose CT screening is recommended for adults ages 50 to 80 who have at least a 20 pack-year smoking history and currently smoke or quit within the past 15 years. A pack-year means packs smoked per day multiplied by years smoked. For example, one pack a day for 20 years equals 20 pack-years.

If you currently smoke, the most powerful intervention remains smoking cessation. Screening helps find lung cancer earlier, but quitting lowers risk across the body.

Prostate Cancer Screening

PSA testing should be a shared decision, not an automatic test for every man. The USPSTF recommends that men ages 55 to 69 make an individual decision about periodic PSA-based screening after discussing possible benefits and harms with a clinician. It recommends against routine PSA-based screening for men age 70 and older.

A family history of prostate cancer, Black ancestry, prior PSA levels, and personal priorities can influence the conversation. A high PSA does not automatically mean cancer, and screening can lead to false-positive results, biopsies, overdiagnosis, and treatment side effects. That is why individualized decision-making matters.

Vaccines Are Preventive Care

Vaccines protect adults from diseases that can cause hospitalization, disability, or death. Your needs depend on age, prior vaccine history, allergies, travel, occupation, chronic conditions, and immune status. Review them during your annual physical.

  • Influenza: Recommended every year.
  • COVID-19: Follow the current CDC schedule and individualized recommendation.
  • Tdap or Td: One adult Tdap dose if not previously received, followed by Td or Tdap boosters every 10 years in most adults.
  • Shingles: Recombinant zoster vaccine is routinely recommended for adults age 50 and older, given as a two-dose series.
  • Pneumococcal: Recommendations are age- and risk-based; adults age 50 and older who have not received a prior pneumococcal conjugate vaccine may be eligible for PCV15, PCV20, or PCV21.
  • RSV: Generally recommended for adults age 75 and older and for certain adults ages 50 to 74 at increased risk of severe RSV disease, using shared clinical decision-making where applicable.

Vaccine recommendations change. Confirm the current CDC schedule with your clinician or pharmacist, particularly if you have heart disease, lung disease, diabetes, kidney disease, cancer, immune suppression, or a history of severe allergic reaction.

Exercise, Strength, and Fall Prevention

Regular movement is one of the most effective preventive tools available. A practical goal for many adults is at least 150 minutes a week of moderate-intensity activity, such as brisk walking, plus muscle-strengthening exercise at least two days a week.

If you are starting from zero, do not wait for the perfect plan. Start with a 10-minute walk after meals or a short daily walk, then build from there. For men in their 60s, 70s, and beyond, strength, balance, mobility, vision, footwear, medication review, and home safety become increasingly important for fall prevention.

Men’s Health by Decade

Age Range What to Review
40s Blood pressure, weight and waist size, cholesterol, diabetes risk, sleep, tobacco and alcohol use, depression, family history, vaccines, and early screening when family history or risk factors justify it.
50s Continue the basics. Confirm colorectal cancer screening. Assess lung cancer screening eligibility if there is a qualifying smoking history. Discuss PSA screening when appropriate. Review shingles and pneumococcal vaccines.
60s Continue chronic disease prevention and cancer screening based on risk and life expectancy. Pay greater attention to medication review, balance, falls, vision, hearing, sleep apnea, bone health risk, and functional strength.
70s and beyond Focus increasingly on function, mobility, fall prevention, cognition, medication burden, bone health, advance care planning, and individualized decisions about ongoing cancer screening.

What to Bring to Your Annual Physical

  • A list of prescription medicines, vitamins, supplements, and over-the-counter products.
  • Your home blood pressure readings, if you monitor at home.
  • Your family history of heart disease, diabetes, colon cancer, prostate cancer, and other major conditions.
  • Your vaccine record, if available.
  • Questions about sleep, mood, sexual health, urinary symptoms, exercise, alcohol, tobacco, and weight changes.

Artificial intelligence tools and online resources can help you organize your questions and understand medical terms. They do not replace a clinician who knows your history, performs an examination, interprets trends, and helps you make decisions in context.

Take Control of Your Health

Your numbers tell a story. Blood pressure, A1C, cholesterol, waist size, exercise habits, vaccine status, and screening history become much more useful when viewed together over time.

Schedule an annual physical near your birthday. Bring your questions. Know your numbers. Small preventive actions taken early can protect your independence and health for years to come.

At Shield Medical Group in Sebring and Lake Wales, Florida, we help adults 50 and older organize preventive care, manage chronic conditions, and make evidence-based health decisions. To schedule a visit, call (863) 236-9550.

Educational only; talk to your clinician.

Frequently Asked Questions

What are the most important health numbers for men?

Key numbers include blood pressure, hemoglobin A1C or fasting glucose, cholesterol values, body mass index, waist circumference, and weight trend. The right interpretation depends on your medical history and overall cardiovascular risk.

How often should men get a physical?

Many adults benefit from an annual preventive visit, especially after age 40 or when they have chronic conditions, medications, risk factors, or overdue screening needs. The frequency of lab testing and follow-up should be individualized.

What blood pressure should a man aim for?

For many adults, a blood pressure below 130/80 mm Hg is a common goal, but the appropriate target depends on age, medical history, medication tolerance, and cardiovascular risk. A clinician should interpret readings collected with proper technique.

At what age should men start colon cancer screening?

Average-risk adults should begin colorectal cancer screening at age 45. Earlier screening may be recommended if you have a family history of colorectal cancer, certain genetic conditions, inflammatory bowel disease, or other risk factors.

Should every man have a PSA test?

No. PSA screening is an individual decision. Men ages 55 to 69 should discuss potential benefits and harms with a clinician. Risk factors such as Black ancestry and a strong family history may make the discussion especially important.

How can I lower my risk of diabetes and heart disease?

Focus on a sustainable pattern: move regularly, include resistance training, avoid tobacco, limit alcohol, improve sleep, manage stress, eat more fiber-rich foods, reduce sugary drinks and highly processed carbohydrates, and work with your clinician to control blood pressure, cholesterol, and blood sugar.

Toenail fungus usually sneaks up on you. One day you spot a little white or yellow mark near the edge of your nail, and it’s easy to brush off. But over time, things can get ugly. The nail thickens, crumbles, changes color, sometimes even starts pulling away from the nail bed.

So, you jump online and find all kinds of DIY remedies—vinegar, tea tree oil, Vicks VapoRub, hydrogen peroxide, baking soda, coconut oil, garlic… the list goes on.

But do any of these actually work?

Some of these home remedies might help keep your feet clean or make it a little harder for fungus to spread. Maybe they even slow things down a bit. But honestly, most natural treatments just don’t go deep enough to wipe out a stubborn toenail fungus infection. Fungus likes to hide underneath or inside the nail, so getting rid of it takes time—and a good dose of patience.

What Is Toenail Fungus?

Doctors call it onychomycosis, but you’ll just know it as a nail that’s turning yellow, white, even brown. The nail gets thick, rough, ragged, and it doesn’t look or smell great. Sometimes it hurts, especially if you let it go for a while.

Why is toenail fungus so common? Your feet stay trapped in socks and shoes all day—warm, dark, kind of sweaty. That’s prime real estate for fungus.

If you’ve ever had athlete’s foot, be careful. The same fungus that causes the skin infection can move into your nails.

Not Every Ugly Toenail Is Fungus

This is a big one. Just because your nail is thick or yellow doesn’t mean fungus is to blame. You might have hurt your toe, your shoes might be pinching, or maybe you’ve got psoriasis. Some bacterial infections can look a lot like fungal ones.

So, before you start dunking your feet in vinegar, check with a healthcare professional. Sometimes they’ll look at your nail or take a small sample to be sure. Guessing isn’t worth it because the wrong treatment does nothing.

Can You Really Cure Toenail Fungus Naturally?

Short answer: There’s no “magic” natural cure. The nail is thick and stubborn—fungus hides deep inside where most remedies don’t reach. Some things like tea tree oil or oregano oil look promising in a petri dish, but that’s not the same as treating your toenail.

In the real world, home remedies help most when you’re keeping nails trimmed, feet dry, and doing everything you can to stop fungus from making itself at home. But for advanced infections, these won’t cut it.

Let’s hit some of the most popular remedies and see where they stand.

1) Tea Tree Oil

Tea tree oil is everywhere online. Lab studies show it can kill fungus in a dish, and a few small human studies have looked at its use for nail fungus. But the evidence just isn’t strong enough to say it cures infections. If you want to try it, don’t put straight tea tree oil on your skin—it burns. Dilute it and stop if your skin gets red, itchy, or irritated.

2) Vicks VapoRub

A lot of people swear by Vicks thanks to its menthol and camphor. Some small studies say it *might* help a little, but again, not a proven cure. Expect nail growth to be slow—don’t wait for an overnight transformation.

3) Vinegar Soaks

Soaking your feet in diluted vinegar “might” help make things less cozy for fungus. But there’s no hard proof that the stuff actually clears an infection. If you try it, always dilute the vinegar. Don’t go overboard with strong solutions—that can hurt your skin.

4) Hydrogen Peroxide

It’s a decent antiseptic, which means it keeps things clean. But there’s no solid evidence it gets rid of fungus in thick, infected nails. If you use it too often or in a strong concentration, expect dried out, irritated skin.

5) Baking Soda

Baking soda is good at soaking up moisture, and that helps make life a little harder for fungus. It doesn’t eliminate what’s already in the nail, but keeping your feet dry is always a plus. Use it to powder your shoes or socks, but don’t expect it to cure an infection.

6) Coconut Oil

Some people use it because it’s gentle and has some antimicrobial action. Will it wipe out toenail fungus? Nope. It’s fine for moisturizing skin, but it isn’t a standalone treatment.

7) Oregano Oil and Garlic

You’ll find these in almost every home remedy roundup. Lab research is interesting, but there’s zero solid evidence they work in real-life toenail fungus. Plus, they can both irritate your skin if you use them carelessly.

8) Keep Your Toenails Trimmed

This one actually helps. If your nails are thick, trimming them makes day-to-day life more comfortable and helps prevent pressure, pain, and further damage. Cut straight across, don’t dig into the sides, and never try to rip off the nail yourself.

9) Control Moisture

Honestly, sweat and dampness make things a hundred times worse. Dry your feet well after showering, wear clean socks every day, rotate your shoes, and steer clear of plastic or non-breathable footwear. Use shower sandals in shared locker rooms or public showers.

10) Treat Athlete’s Foot

Athlete’s foot can jump from the skin to your toenails. If your toes are itchy, peeling, or cracked, treat that right away with an over-the-counter antifungal cream—and follow the directions. Treating only the nail while ignoring the skin lets the fungus keep looping back.

11) Clean Your Tools and Shoes

Don’t share nail clippers or files. Wash your towels and disinfect nail tools after each use, especially if you’re dealing with fungus. Let shoes air out and dry completely before wearing them again.

Skip DIY Bleach “Cures” and Harsh Chemicals

Don’t put bleach, undiluted hydrogen peroxide, or aggressive chemicals near your toes. Not only do these not work, but they can actually burn or seriously irritate your skin.

Are “10 Minute Cures” Real?

Nope. If you see a product claiming you’ll have fungus-free nails in a matter of minutes or overnight, scroll on by. Your toenail grows super slowly. Even after the infection is gone, the damaged part has to grow out—and that can take months.

Safe Home Treatment Routine

If you catch things early and want to try conservative care, focus on a simple routine:

Wash and dry your feet morning and night. Change your socks daily. If you use a topical remedy, follow the instructions. Trim nails straight and clean your tools. Take progress photos every few weeks so you can see if things are improving.

How Do You Know If Things Are Getting Better?

Don’t just watch the older, damaged part of the nail. Look at the base—new, healthy nail means you’re on the right track. It can take months for clear progress, so patience really matters. If the infection is spreading or you’re not seeing changes, it’s time for professional advice.

When Home Remedies Aren’t Enough

If more than one toenail is involved, the nail is super thick, painful, separating, or you have other health problems (like diabetes or poor circulation), get medical help. Same if you just don’t know what’s going on, or if you’re hitting a wall with home treatments.

Medical Options

Doctors can prescribe stronger antifungals. Topical meds are an option, but pills work faster for tough infections. There are side effects, so let your doctor decide what’s safest for you. Don’t buy prescription pills online and try them on your own.

Keeping Fungus From Coming Back

Once you’ve gotten rid of fungus, prevention is everything. Dry feet, trimmed nails, clean tools, breathable shoes, and treating athlete’s foot quickly will save you lots of headaches in the future.

Frequently Asked Questions

Q. What’s the best home remedy for toenail fungus?
No guaranteed fix. Tea tree oil and Vicks are talked about the most. Keeping feet dry and nails trimmed helps.

Q. Can Vicks cure it?
Evidence is weak, but some people notice small improvements.

Q. Does hydrogen peroxide work?
Not really, and too much can damage your skin.

Q. How about vinegar?
Maybe a little, but there’s no proof it cures real nail infections.

Q. Can I yank off my own toenail?
Don’t. If the nail absolutely has to come off, that’s for a doctor to do.

Q. How long does it take to clear up?
Expect months, even with prescription treatments, because nails just take forever to grow out.

Final Takeaway

If you go searching online, you’ll find hundreds of “miracle cures” involving everything from garlic to mouthwash. The truth? Most home remedies don’t do much beyond basic hygiene or minor help. The reliable, sensible stuff is boring—keep your feet dry, nails trimmed, treat athlete’s foot, and clean your tools.

If the fungus isn’t going away, or if you’re noticing pain, spreading, or you have conditions like diabetes, don’t put off seeing a doctor. Toenail fungus is annoying and stubborn, but with consistent, careful treatment, you’ve got a good shot at healthier nails. Don’t fall for magic cures—stick with what works and be patient.

Waking up with a swollen, painful knee can really catch you off guard—especially if you don’t remember getting injured. Most people start worrying about arthritis, ligament trouble, or just plain old aging joints. But there’s another culprit that often gets overlooked: gout. And yes, it doesn’t just go after your big toe. Gout can settle right into your knee, turning it red, swollen, and so sore you barely want to move.

So, what’s going on? Gout in the knee is basically uric acid crystals piling up inside your joint and sparking inflammation. That means your knee can get hot, stiff, and seriously painful, sometimes out of nowhere.

Luckily, this isn’t a hopeless situation. With the right diagnosis, medication, a few lifestyle tweaks, and some smart prevention, most people can keep gout attacks at bay and protect their knees from long-lasting damage.

Here’s what you need to know—what causes gout in the knee, what it feels like, how doctors figure it out, how long it sticks around, treatment, home care, and tips to avoid it coming back.

What Exactly Is Gout in the Knee?

Gout in knee is a form of inflammatory arthritis caused when uric acid crystals collect inside the joint. Normally, when your body breaks down purines, it makes uric acid—which the kidneys are supposed to clear out. But sometimes you end up with too much, or your kidneys just can’t keep up, and uric acid starts building up in your blood.

You wait long enough with high uric acid and those sharp, jagged crystals start settling in your joints. Your immune system freaks out and launches a full-on inflammation attack—which is where the pain, swelling, and stiffness come from.

People usually expect gout in their toe, but it’s not picky—it can show up in your knees, ankles, feet, wrists, fingers, and even elbows. The knee is fair game because it’s got just the right fluid environment for crystals to gather and cause trouble.

Can Gout Really Strike Your Knee?

Absolutely. Most folks get their first taste of gout in the big toe, but knees are prime targets too. Those uric acid crystals can build up inside the main joint, around the kneecap, along the sides, or even in the soft tissues and tendons nearby.

When the crystals irritate everything, your knee gets inflamed—pain and swelling usually come on fast. Unlike regular knee pain that creeps up, gout delivers that knockout punch in hours.

What Triggers Gout in the Knee?

It comes down to uric acid crystals forming inside your knee joint—but a bunch of factors can set you up for it.

1) High Uric Acid Levels

If your uric acid is high (that’s hyperuricemia), you’re at risk. Crystals form when levels get too concentrated. But not everyone with high uric acid gets gout—some folks never show symptoms unless the crystals actually cause inflammation.

2) Food and Diet

Some foods have stacks of purines, which your body turns into uric acid. These offenders include red meat, organ meats, shellfish, fatty seafood, beer, and sugary soft drinks. Eating one steak isn’t going to bring on gout—usually it’s years of high uric acid and other risk factors adding up.

3) Kidney Function

Your kidneys are supposed to filter out excess uric acid. If they’re slacking off or you’ve got kidney troubles, uric acid builds up and crystals form.

4) Genetics

Family history matters. If gout runs in your family, your odds go up.

5) Other Health Conditions

Obesity, high blood pressure, diabetes, metabolic syndrome, heart disease, and kidney disease can all mess with how your body handles uric acid.

Gout in the Knee: Symptoms

Gout knee pain is no joke, and it tends to hit hard and fast—sometimes overnight.

1) Major Knee Pain

We’re talking agony—enough to make walking, standing, climbing stairs, bending your knee, or even sleeping a major ordeal. Just brushing against your knee can hurt.

2) Swelling

Expect to see your knee balloon up. The skin gets tight, movement stiffens, and the joint swells from extra fluid thanks to inflammation.

3) Redness and Heat

Your knee turns red and hotter than the surrounding skin. That’s your immune system bringing more blood to the fight.

4) Limited Motion

Swelling and pain can make fully bending or straightening your knee almost impossible.

5) Nighttime Attacks

Gout tends to sneak up at night or early morning—you go to bed feeling fine, wake up feeling miserable.

Elderly woman holding painful knee showing possible gout-related joint pain

Gout vs. Other Knee Issues

Not all nasty knee pain is gout. You might be dealing with osteoarthritis, rheumatoid arthritis, injuries, bursitis, tendon problems, infection, or pseudogout. Some people may also experience other symptoms like knee numbness or unusual sensations, which can have different causes and may require medical evaluation. But gout brings its own flavor—a sudden smack of pain, fast swelling, redness, warmth, all tied to those uric acid crystals. Doctors usually need some tests to confirm it’s gout.

How Do Doctors Diagnose Gout in the Knee?

They’ve got a few strategies.

1) Joint Fluid Test

This is the gold standard. They draw a bit of fluid from your swollen knee and look under a microscope for uric acid crystals. If they find them, it’s gout. This also helps rule out infection.

2) Blood Test

Measuring your blood’s uric acid helps, but isn’t the final word. Some people have normal levels during a flare-up, or high levels without symptoms. Docs use test results plus your symptoms, medical history, and exam.

3) Imaging

They might use ultrasound, dual-energy CT scans, or X-rays. An X-ray can show joint damage or crystal deposits if gout has been around a while—but early attacks don’t always show up.

How Long Does Gout in the Knee Last?

Usually, if you don’t treat it, a single gout attack lasts about 3 to 10 days—sometimes stretches to two weeks or more. The worst pain is within the first couple days, then things slowly get better. But without proper treatment, attacks can keep coming. They might stick around longer, show up in other joints, or eventually start damaging things permanently.

Don’t just live with repeated attacks.

Treating Gout in the Knee

There are two big goals: stop the pain and inflammation, and prevent more gout attacks.

1) Medicines for a Flare-Up

Doctors often suggest NSAIDs, colchicine, or corticosteroids. What’s best depends on your health, kidney function, and any other medical issues.

2) Rest and Ice

Don’t put weight on your knee if the pain is bad. Cut back on activity, wrap an ice pack in a towel and rest it on your knee, and keep your leg raised. All these can help with pain and swelling.

3) Long-Term Medication

If you keep getting gout, you’ll probably need meds to keep uric acid down.

4) Allopurinol

This drug lowers uric acid production and is commonly used for long-term management.

5) Febuxostat

Works in a similar way and can be recommended.

6) Colchicine

Used both during flares and sometimes to prevent them when starting new treatment.

Always stick to your doctor’s advice—don’t try to manage this on your own.

Taking Care of Gout in the Knee at Home

Home care won’t dissolve those crystals right away, but you can support your treatment with healthy habits:

1) Drink More Water

Good hydration keeps your kidneys working and helps get rid of waste.

2) Maintain a Healthy Weight

Extra weight raises uric acid and strains joints.

3) Eat Wisely

Fill your diet with vegetables, whole grains, low-fat dairy, fruits, and lean proteins.

4) Watch Out for Alcohol and Sugar

Avoid booze and sugary drinks—they increase gout risk.

Preventing More Gout

Consistency matters. Keep an eye on your uric acid, eat right, limit purine-heavy foods, drink plenty of water, exercise regularly, and take meds as prescribed. On days without flare-ups, try walking, swimming, or cycling—they’re easy on the knees.

FAQs About Gout in the Knee

Q. Can you get gout in your knee?
Yep. Uric acid crystals can pile up and make your knee ache, swell, and get inflamed.

Q. What are the first signs?
Sudden pain, swelling, heat, redness, stiffness, and trouble moving your knee.

Q. Does uric acid cause joint pain?
Definitely, when it forms crystals that kick off inflammation.

Q. Can gout permanently damage the knee?
Yes—if attacks keep happening and go untreated, the joint can suffer for the long haul.

Q. Is gout the same as arthritis?
Gout is a type of inflammatory arthritis, but not the same as osteoarthritis (the “wear-and-tear” kind).

Final Thoughts

Gout in the knee hurts like hell, but it doesn’t have to wreck your life. Spot the symptoms early, get checked, follow your treatment plan, and stick with healthy habits. That’s the best way to keep attacks from coming back and protect your knee for the future.

If your knee suddenly swells up and hurts, don’t brush it off—get help. Early treatment is your best shot at keeping gout under control and staying on your feet.

By Kulmeet Kundlas MD, Board-Certified Internal Medicine — Shield Medical Group, Sebring and Lake Wales, Florida

Two or three times a day, a patient asks me the same question when we review their blood work:

“Doctor, what are the prediabetes symptoms I should watch for?” Here is the honest answer most patients never hear — prediabetes has no direct symptom. It is silent. But your body does leave clues, and if you know where to look, you can catch it early and reverse it.

In this article I will walk you through what prediabetes actually is, how insulin resistance quietly damages your metabolism, the seven warning signs that suggest you may be prediabetic, and what you can do to put it into remission before it becomes type 2 diabetes.

Watch Dr. Kundlas explain prediabetes symptoms and warning signs:https://youtu.be/d4qIqUR1wz0

What Prediabetes Really Means

Prediabetes is the stage where your blood sugar is higher than normal, but not yet high enough to be called diabetes. It is a warning that your body is losing the ability to handle glucose, and it is driven by insulin resistance.

People often expect a specific symptom, like a rash or a pain. There isn’t one. Symptoms imply you walked into a clinic with a complaint. Nobody walks into my office saying, “I feel prediabetic.” You come in for something else, or your annual blood work picks it up. That is precisely why it is dangerous — it hides until real damage begins.

According to the Centers for Disease Control and Prevention, more than 1 in 3 American adults have prediabetes, and most of them don’t know it. That is the real problem. Silent doesn’t mean harmless.

How Insulin Resistance Works

Think of insulin as a key. Your cells have locks called insulin receptors. When insulin binds to those receptors, the door opens and glucose walks into the cell to be used for energy. In insulin resistance, the lock becomes sticky. Sometimes it opens, sometimes it doesn’t. Sugar starts backing up in your bloodstream.

Four organs work together to control your blood sugar:

  • Pancreas — the factory that produces insulin
  • Liver — stores glucose and releases it when you fast
  • Muscle — the biggest sink for glucose after meals
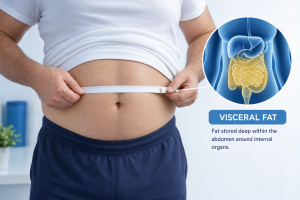
  • Visceral fat — the fat around your organs, which drives inflammation

The sugar in your blood comes from two places. First, what you eat. Second, what your liver makes by breaking down stored glycogen and converting protein into glucose. This is a survival system so your brain never runs out of fuel. But when the liver becomes insulin resistant, it keeps pumping out glucose even when it shouldn’t. That is why fasting sugars rise first in most people.

What happens in each organ

  • Liver: Ignores insulin’s signal to stop making glucose. Your fasting sugar climbs.
  • Muscle: Stops pulling sugar out of the blood efficiently. Your post-meal sugar stays high for hours.
  • Visceral fat: Releases inflammatory chemicals and free fatty acids that make insulin resistance worse.
  • Pancreas: Compensates by pumping out more insulin, which works for a while, until it eventually tires out.

How Prediabetes Is Diagnosed

Diagnosis is not based on how you feel. It is based on blood work. According to the American Diabetes Association, any of the following puts you in the prediabetes range:

  • Fasting blood glucose: 100 to 125 mg/dL
  • Hemoglobin A1C: 5.7% to 6.4%
  • Oral glucose tolerance test (2-hour value): 140 to 199 mg/dL

If your numbers cross those upper limits, you are no longer prediabetic — you have type 2 diabetes. To understand what A1C actually measures and why it matters, read our companion article on what your A1C really measures.

7 Warning Signs Your Body May Be Giving You

You will not “feel” prediabetes the way you feel a cold. But your body does whisper. Here are the seven clues I look for in the exam room.

1. Your Waist Is Growing

An expanding waistline is the single most useful clue I see in clinic. It reflects visceral fat — the fat wrapped around your liver, pancreas, and intestines. That fat is not passive storage. It is metabolically active, and it releases inflammatory chemicals and free fatty acids into your bloodstream. The result is a worsening cycle: more visceral fat leads to more inflammation, more insulin resistance, and higher blood sugar.

A rough clinical target for adults is a waist circumference under 40 inches for men and under 35 inches for women. If your belt keeps loosening in the wrong direction, take it seriously.

2. Dark, Velvety Patches on Your Skin

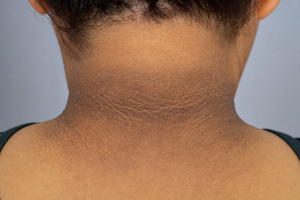
This is called acanthosis nigricans. You will see it on the back of the neck, in the armpits, or in the groin. The skin looks dirty even after scrubbing, feels thick and velvety, and often has small skin tags nearby. It is not a hygiene problem. It is a walking billboard for insulin resistance.

When your muscles, liver, and fat resist insulin, the pancreas compensates by producing more of it. High insulin levels stimulate skin cells called keratinocytes and fibroblasts to multiply, which creates those dark, thickened patches. If you see this on your neck or armpits, ask your doctor to check your fasting glucose and A1C.

3. Constant Fatigue That Doesn’t Match Your Sleep

Blood sugar that spikes and crashes will wear you out. You feel tired after meals, sluggish in the afternoon, and never quite rested even after a full night in bed. Insulin resistance also raises your risk of sleep apnea, poor sleep quality, and low mood, which pile onto the fatigue.

Yes, many things cause fatigue — thyroid disease, anemia, depression, sleep apnea. But if those tests are normal and your sugar markers are creeping up, prediabetes is often hiding behind the tiredness.

4. Constant Hunger and Carb Cravings

You eat, and an hour later you’re hungry again. You crave bread, chips, sweets, sugary drinks. That is not a willpower problem. When insulin can’t get glucose into your cells, your brain reads it as “starving” and pushes you toward the fastest source of energy — simple carbs. The cycle repeats and your visceral fat grows.

5. Increased Thirst

When blood sugar rises high enough, your kidneys start dumping glucose into your urine. Water follows the sugar out, so you get dehydrated and thirsty. If you notice this symptom, the window for “just prediabetes” is closing. You may already be moving into type 2 diabetes.

6. Frequent Urination

Waking up two or three times a night to urinate is not normal for most healthy adults. It happens with prediabetes moving toward diabetes because the kidneys are working overtime to clear excess sugar. Combined with increased thirst, this is a red flag.

7. Blurred Vision or Slow-Healing Wounds

These are late signs and usually mean you have already crossed from prediabetes into diabetes. High sugar changes the shape of the lens in your eye and slows the immune cells that repair skin. If you notice either one, do not wait for your annual physical. Get your blood work done now.

The Good News — Prediabetes Is Reversible

This is the part I want you to hear clearly. Prediabetes is not a death sentence. It is a warning shot, and you can respond.

Landmark evidence from the Diabetes Prevention Program showed that adults with prediabetes who lost about 7% of their body weight and walked roughly 150 minutes per week cut their risk of developing type 2 diabetes by 58%. That is a bigger effect than most medications.

Practical steps that work:

  • Lose 5% to 7% of your body weight if you carry extra weight, especially around the belly.
  • Walk 30 minutes after your largest meal. A post-meal walk lowers blood sugar more than you would expect.
  • Cut simple carbs and sugary drinks. Focus on protein, vegetables, and fiber. Our fiber guide explains why fiber is your ally.
  • Sleep 7 to 8 hours. Poor sleep alone worsens insulin resistance.
  • Get rechecked in 3 to 6 months. Track your A1C, fasting glucose, and waist size.

Some patients also benefit from medications like metformin or, in select cases, GLP-1 medications. That decision belongs in a conversation with your primary care physician who knows your full picture.

What to Do Next

If any of these seven clues sound like you, do not wait for symptoms that never come. Ask your primary care physician for a fasting glucose and hemoglobin A1C. If you don’t have a primary care doctor, this article explains why that gap matters.

At Shield Medical Group in Sebring and Lake Wales, Florida, we work with adults 50 and older every day on exactly this — catching prediabetes early, reversing it when possible, and preventing the complications of diabetes. If you would like to be seen, call (863) 236-9550 or visit our clinic.

Frequently Asked Questions

Can prediabetes be reversed?

Yes. Losing 5% to 7% of your body weight, walking regularly, and cutting simple carbs can return your A1C and fasting glucose to normal in many people. The earlier you act, the higher your chance of remission.

What is the A1C range for prediabetes?

Prediabetes is defined as a hemoglobin A1C between 5.7% and 6.4%. An A1C of 6.5% or higher on two separate tests is diagnostic of type 2 diabetes.

Does prediabetes always turn into diabetes?

No. Without lifestyle change, roughly 1 in 3 adults with prediabetes progress to type 2 diabetes within 5 years, according to the CDC. With focused weight loss and activity, most people can prevent or delay it significantly.

Is acanthosis nigricans always caused by prediabetes?

No, but insulin resistance is the most common cause in adults. Rarely, it can be linked to certain medications or other medical conditions. Ask your physician to check your fasting glucose and A1C first.

How often should I get checked if I have prediabetes?

Most guidelines recommend rechecking fasting glucose and A1C every 3 to 6 months when you are actively working on lifestyle change, and at least once a year otherwise.

The Bottom Line

Prediabetes does not shout. It whispers through your waistline, your skin, your energy, and your cravings. Listen early, act early, and you can rewrite the ending.

Ever bite into a lemon and instantly feel your lips pucker and your mouth water? Maybe your eyes squint, too. That’s the unmistakable punch of sour foods.

But lemons aren’t the only foods that make your face twist. Sour flavors pop up everywhere—limes, grapefruit, tamarind, green mango, yogurt, pickles, vinegar, cranberries, and pretty much anything fermented can give you that sharp, tangy kick.

Some foods come by their sourness naturally—they’re loaded with acids. Others get that way through fermentation or the way they’re prepared.

So what’s really going on? What makes something taste sour? And which foods are the sourest of all?

Let’s break it down. This guide covers a full rundown on sour foods, a list of popular sour fruits, healthier sour snacks, how sour and tart differ, and the science behind what makes our tastebuds tingle.

What Exactly Is Sour?

Sour is one of those basic tastes we pick up right away. You know the feeling—a sharp, tangy rush that hits your tongue when you bite into a lemon, splash vinegar on a salad, or grab a spoonful of yogurt. That zing? It’s all about acids.

Different foods bring different acids to the table. Lemons, limes, oranges, and grapefruits hit you with citric acid. Apples, cherries, and a bunch of berries pack malic acid. Grapes and tamarind have tartaric acid. Yogurt and other fermented stuff? Lactic acid. Then there’s vinegar, famous for its punchy acetic acid.

But acidity isn’t the whole story. Sugar can counterbalance sourness. That’s why an orange, which actually has acid, tastes sweet compared to a lemon.

What Makes Food Taste Sour?

The short answer: acids.

Here’s what happens: When you eat something acidic, it releases hydrogen ions in your mouth. Your taste buds pick them up and fire off a “wow, that’s sour!” message to your brain.

Still, the way each acid hits is a bit different. Citric acid gives lemons and limes their clean, sharp edge. Malic acid is behind that bright tartness in green apples. Acetic acid? That’s the bite in vinegar.

That’s also why sour candy tastes its own kind of sour—manufacturers use a blast of citric or malic acid for an ultra-intense hit.

Sour vs. Tart: So, What’s the Difference?

People go back and forth between “sour” and “tart,” but there’s a small difference. Sour is usually stronger and more mouth-puckering. Tart is sharp, but often a bit more balanced, maybe with some sweetness or fruitiness hanging around.

Sour things: lemon juice, vinegar, pickle juice, sour candy.

Tart things: green apples, cranberries, tart cherries, pomegranate.

So if you call something tart, you probably mean it’s sour, just not knock-your-socks-off sour.

Sour vs. Bitter

Sour and bitter are totally different ball games. Sour comes from acidity. Bitter is a different taste, from different compounds, picked up by different taste buds.

A lemon? That’s sour. Black coffee? Bitter. Grapefruit? Somehow, both.

“Bitter” tends to be a turn-off for many people, which is why bitter foods often need sugar or salt to balance the flavor.

What About Tangy?

Tangy is that lively, pleasantly sharp taste. It’s not usually as intense as “sour” (think lemon juice) but still has enough edge to make things interesting.

Yogurt is tangy. Salsa, chutney, pickles, mustard, salad dressings—many of those sit in the tangy zone, blending acidity with sweetness, salt, or spice.

25 Sour Foods to Know

Here’s a list to make your mouth water (or pucker):

1. Lemons – The classic. Full of citric acid, used everywhere from lemonade to salad dressings.

2. Limes – Another sour superstar, perfect in drinks, curries, desserts, and sauces.

3. Grapefruit – Not just sour; it’s got sweetness and bitterness, too.

4. Tamarind – Tangy to the extreme when unripe, but gets sweeter as it matures. Amazing in chutneys, drinks, and curries.

5. Green Mango – Crunchy and mouth-puckering when unripe; a staple in many Asian salads and snacks.

6. Cranberries – Naturally tart, almost astringent; often sweetened in juice and sauces.

7. Gooseberries – Can swing from mild to extreme in the tart department, especially when green.

8. Green Apples – Tart, crisp, with just enough sweetness to keep you coming back.

9. Tart Cherries – Much more acidity than sweet cherries; great in juices, pies, and jams.

10. Passion Fruit – Sweet-tart, aromatic, and intense; makes juices pop.

11. Kiwi – The sourness ramps up if it’s a bit underripe.

12. Pineapple – Sweet and juicy, but definitely rocking some natural acidity.

13. Sour Oranges – Some varieties are surprisingly tangy and excellent for marmalades or marinades.

14. Pomegranate – Sweet-tart seeds, varying depending on the fruit’s ripeness.

15. Red Currants – Tiny, jewel-like berries with a bright tart punch.

16. Rhubarb – So tart it’s rarely eaten raw; usually paired with sugar in desserts.

17. Vinegar – Packs a sharp, nose-tingling sourness thanks to acetic acid.

18. Pickles – Sour from vinegar or fermentation, often both.

19. Yogurt – Fermented, with a gentle, ongoing tang.

20. Kefir – Like yogurt, but usually sharper and a bit effervescent.

21. Kimchi – Gets more acidic as it ferments; a little spicy, a little salty, a little sour.

22. Sauerkraut – Cabbage transformed into a tangy, crunchy sidekick through fermentation.

23. Sourdough Bread – That signature “tang” comes from acids made by wild fermentation.

24. Sour Cream – Rich, smooth, with gentle, creamy acidity.

25. Sour Candy – Not exactly healthy, but unforgettable for its face-twisting intensity.

Sour Fruits: The Greatest Hits

Wondering what fruits push the sour button? Try:

  • Lemon
  • Lime
  • Grapefruit
  • Tamarind
  • Cranberry
  • Gooseberry
  • Green apple
  • Green mango
  • Tart cherry
  • Passion fruit
  • Kiwi
  • Pineapple
  • Pomegranate
  • Red currant
  • Sour orange
  • Kumquat
  • Calamansi

Fruit doesn’t stay at the same sourness forever, though. Ripeness and variety play a huge role—an underripe kiwi is way more sour than a ripe one.

What’s Citrus, Anyway?

Citrus means fruits like lemons, limes, oranges, grapefruit, mandarins, pomelos—all those sunny, zesty guys.

“Citrus” doesn’t mean “sour” automatically. Oranges, for example, have acid but taste sweet because of all their sugar.

What Foods Really Have Citric Acid?

Citric acid is all over the citrus family:

– Lemons
– Limes
– Oranges
– Grapefruit
– Tangerines
– Pomelos

And you’ll also spot it as an ingredient in sodas, candies, and processed foods (it adds acidity or helps with preservation). There’s even a powder called “sour salt,” which is just food-grade citric acid—totally different from actual salt.

The Sourest Foods in the World

There’s no universal champ, but if you want seriously sour, try:

– Lemon or lime juice
– Unripe tamarind
– Green mango
– Cranberries
– Gooseberries
– Umeboshi (pickled Japanese plum)
– Bitingly strong vinegar
– Super sour candies

Basically, anything loaded with acid and not much sugar makes the list.

Looking for Healthy Sour Foods?

Not all sour flavors are created equal. A wedge of fresh kiwi and a sour gummy both taste tangy, but only one packs vitamins and fiber.

Healthy sour foods and fresh fruits

Some good-for-you sour snacks:

– Plain yogurt—throw in some berries!
– Green apple slices
– Kiwi
– Grapefruit
– Pomegranate
– Mixed berries
– Pineapple
– Green mango
– Pickled or fermented veggies (kimchi, sauerkraut, etc.)
– Cucumber spritzed with lemon or lime

These sour foods can be part of a varied, nutrient-rich diet. If you’re looking for more nutritious options, check out our guide to foods that increase blood flow for more ideas.

Why Do I Crave Sour Foods?

Cravings are a bit of a mystery—maybe you just love the refreshing jolt, or you’re bored of bland foods. Sometimes, people crave sour flavors for the wake-up-it-gives-your-mouth feeling.

If you’re craving nothing but sour all the time and it worries you, check in with a professional. Otherwise, it’s probably just about personal taste.

How to Fix Foods That Are Too Sour

Oops—too much lemon or vinegar in your recipe? You can rescue your meal:

– Add something sweet—sugar, honey, even a dash of maple syrup.
– Dilute—add more of the main, non-sour ingredients (broth, veggies).
– Stir in something rich—cream, coconut milk, butter (especially in curries and sauces).
– Add bulk—rice, potatoes, beans, other mild ingredients will mellow things out.

The idea isn’t to scrub out all the acid, just to restore balance.

Is Sour Food Spoiled Food?

Nope! Plenty of foods are SUPPOSED to be sour. Yogurt, kefir, kimchi, sauerkraut, sourdough—that sourness happens thanks to controlled fermentation.

Spoiled foods, on the other hand, can develop an odd sour smell or taste unexpectedly—and that’s not safe. If you ever doubt food safety, toss it. Don’t risk it.

The Fruit That Makes Sour Taste Sweet

Here’s something wild: miracle fruit. It’s a berry (Synsepalum dulcificum) that messes with your taste buds. Eat one, then bite into a lemon, and suddenly—lemons taste sweet! Your brain gets tricked for a while. The fruit doesn’t add sugar to the lemon; it just temporarily changes your taste perception.

Quick Questions, Quick Answers

Q. What’s a sour food?
Anything with a strong acidic flavor—lemons, limes, vinegar, yogurt, pickles.
Q. Popular sour foods?
Lemons, limes, grapefruit, tamarind, green mango, cranberries, yogurt, vinegar, pickles, kimchi, and sauerkraut.
Q. What’s a sour fruit?
Lemon, lime, grapefruit, tamarind, cranberry, gooseberry, green mango, tart cherry, passion fruit.
Q. Are lemons sour?
Big time.
Q. Is grapefruit sour?
Yes, and sometimes bitter, too.
Q. Is citric acid sour?
Absolutely—the main reason citrus tastes the way it does.
Q. What is sour salt?
Food-grade citric acid powder.
Q. Sour vs. bitter?
Sour = acidic; bitter = different taste entirely.
Q. Is tart just a milder sour?
Pretty much.
Q. What does tangy taste like?
Pleasantly sharp, lively, a bit acidic (yogurt, pickles, chutneys).
Q. Can I eat sour foods?
Most natural sour foods are fine for most people! Just consider the food overall, and your own needs.

Final Thoughts

Sour foods are everywhere—lemons, limes, tamarind, green mango, cranberries, yogurt, pickles, kimchi, sauerkraut, sourdough bread… they all bring acidity and excitement to your plate.

Acids like citric, malic, lactic, and acetic drive those flavors, but sugar, ripeness, and other ingredients change how you experience them.

If you want to eat more healthy sour foods, go for fresh fruits, regular yogurt, and good-for-you fermented fare—not just whatever seems most mouth-puckering.

The best sour food doesn’t just make you wince—it should keep you coming back for another bite.

Moderna mFlusiva mRNA Flu Vaccine: FDA Approval, Effectiveness and Safety

Moderna’s mFlusiva is the first FDA-approved mRNA influenza vaccine for adults age 50 and older. Here is what the clinical evidence actually shows about effectiveness, safety, approval status, and the future of flu vaccination.

Medical disclaimer: This article is for education only and is not personal medical advice. Vaccination decisions should be made with your physician, pharmacist, or qualified healthcare professional, especially if you have a history of severe allergic reaction, immune suppression, or complex medical conditions.

Key Takeaways

  • FDA approved Moderna’s mFlusiva, also called mRNA-1010, for adults age 50 and older.
  • In a Phase 3 trial of 40,805 adults age 50+, mFlusiva showed 26.6% greater relative protection against PCR-confirmed influenza-like illness than a standard-dose flu vaccine.
  • The primary trial compared mFlusiva with a standard-dose vaccine, not a high-dose flu vaccine.
  • Adults age 50 to 64 received traditional FDA approval. Adults age 65 and older received accelerated approval, pending confirmation of clinical benefit in a postmarketing study.
  • Injection-site pain, fatigue, and headache occurred more often with mFlusiva, but most reactions were mild to moderate and short-lived.
  • An mRNA flu vaccine does not contain live influenza virus and cannot cause influenza infection.

What Is Moderna’s mFlusiva?

mFlusiva is Moderna’s mRNA-based seasonal influenza vaccine, scientifically known as mRNA-1010. It is designed to protect against influenza A/H1N1, influenza A/H3N2, and influenza B/Victoria strains represented in the seasonal vaccine formulation.

Unlike traditional egg-based influenza vaccines, mFlusiva uses messenger RNA packaged inside lipid nanoparticles. The mRNA provides temporary instructions that allow the body’s cells to make influenza hemagglutinin proteins, which train the immune system to recognize and respond to influenza viruses in the future.

The vaccine is given as a single intramuscular injection and is approved for adults age 50 and older.

FDA Approval: What It Means

The FDA approved mFlusiva through two different regulatory pathways. Understanding this distinction is important, especially for older adults deciding which flu vaccine may be appropriate for them.

Age Group FDA Approval Pathway Primary Evidence Used
Adults 50 to 64 years Traditional approval Clinical efficacy against PCR-confirmed influenza-like illness compared with a standard-dose flu vaccine
Adults 65 years and older Accelerated approval Superior immune responses compared with high-dose Fluzone, plus supportive clinical-efficacy data

For adults 65 and older, the FDA requires Moderna to conduct a confirmatory postmarketing study to verify and describe the vaccine’s clinical benefit. This is not unusual for accelerated approval, which permits earlier access when a product shows a favorable benefit-risk profile based on a surrogate marker reasonably likely to predict benefit.

Important clarification: “Accelerated approval” does not mean the vaccine skipped safety review. It means the FDA allowed use in adults age 65 and older based primarily on superior immune-response data while requiring additional clinical-outcome data after approval.

How Effective Was the mRNA Flu Vaccine?

Moderna’s pivotal Phase 3 trial enrolled 40,805 adults age 50 and older. Participants received either mFlusiva or a licensed standard-dose influenza vaccine and were followed through the 2024–2025 flu season.

Outcome mFlusiva Group Standard-Dose Comparator
Participants with PCR-confirmed influenza-like illness 2.0% (411 of 20,179) 2.8% (557 of 20,124)
Relative vaccine efficacy 26.6% greater relative protection for mFlusiva
Adults age 65 and older subgroup 27.4% relative vaccine efficacy versus standard-dose flu vaccine

In plain language, people who received mFlusiva had fewer confirmed influenza-like illnesses than people who received the standard-dose comparator vaccine. The 26.6% number is a relative improvement compared with another vaccine, not a claim that mFlusiva prevents 26.6% of all flu illness in every population or every season.

The study also found fewer influenza-related healthcare encounters in the mRNA-vaccine group. However, hospitalization events were uncommon, so the trial was not designed to establish a precise reduction in hospitalization risk alone.

Was It Better Than High-Dose Flu Vaccine?

This distinction matters because adults age 65 and older are commonly offered enhanced influenza vaccines, including high-dose, adjuvanted, or recombinant flu vaccines.

The major 40,000-person clinical-efficacy trial compared mFlusiva with a standard-dose influenza vaccine. It did not directly prove that mFlusiva reduces clinical flu illness more than high-dose flu vaccine in seniors.

In a separate Phase 3 study involving adults age 65 and older, mFlusiva produced higher hemagglutination-inhibition antibody responses than high-dose Fluzone against all four vaccine-matched strains. These immune-response findings supported accelerated approval for this age group, while a confirmatory clinical-efficacy study is planned.

Why Do We Need New Flu-Vaccine Technology?

Influenza changes continuously. Small genetic changes over time are called antigenic drift. Major changes, usually involving influenza A viruses, are called antigenic shift and can contribute to pandemic risk.

Each year, global health authorities select influenza strains for the upcoming season based on surveillance data. This is a science-based forecasting process, not random guessing. However, a mismatch can occur if circulating viruses change after strain selection or if vaccine production introduces changes that make the vaccine antigen less similar to circulating viruses.

Many traditional flu vaccines are produced in eggs. During egg-based manufacturing, some influenza viruses can acquire egg-adaptive changes that may affect how closely the vaccine antigen resembles the virus circulating in people. Cell-based and recombinant vaccines already reduce some of these limitations. mRNA technology offers another approach.

Potential Advantages of mRNA Technology

  • It does not require growing influenza viruses in chicken eggs.
  • It may avoid egg-adaptive changes that can affect antigen matching.
  • It may allow faster manufacturing and later strain selection before flu season.
  • It offers a flexible platform that can be updated as circulating viruses evolve.
  • It provides an egg-free option for people who prefer to avoid egg-based vaccine production.

Importantly, mRNA technology does not eliminate antigenic drift or antigenic shift. Influenza viruses will continue to evolve. The potential benefit is that mRNA platforms may help vaccine manufacturers respond more quickly and precisely to those changes.

How Does an mRNA Flu Vaccine Work?

A useful analogy is a temporary recipe card. The vaccine delivers mRNA instructions into cells near the injection site. Those cells briefly use the instructions to make a harmless influenza protein target called hemagglutinin.

The immune system sees that protein, creates antibodies and immune memory, and then the mRNA instructions break down naturally. The mRNA does not enter the cell’s nucleus, does not alter a person’s DNA, and does not remain in the body long term.

Can mRNA Flu Vaccine Cause the Flu?

No. mFlusiva does not contain live influenza virus. It cannot reproduce in the body and cannot cause influenza infection. Some people may develop short-term immune-related symptoms such as soreness, fatigue, headache, body aches, or mild fever after vaccination. These reactions are not influenza illness.

mFlusiva Safety: What Did the Trials Show?

The FDA reviewed safety data from multiple Phase 3 trials, including an integrated safety analysis involving more than 70,000 participants age 50 and older. The mRNA vaccine produced more short-term local and systemic reactions than standard-dose or high-dose comparator vaccines, but most reactions were mild to moderate and resolved quickly.

Common Reaction What Patients May Experience Typical Duration
Injection-site reaction Pain, tenderness, swelling, or redness Usually brief
Systemic symptoms Fatigue, headache, muscle aches, chills, or low-grade fever Usually 1 to 2 days
Serious adverse events Uncommon and overall balanced between study groups Requires medical assessment when present

In the pivotal study, the most commonly reported reactions among mFlusiva recipients included injection-site pain, fatigue, and headache. Across the broader clinical program, rates of serious adverse events and adverse events of special interest were generally balanced between mFlusiva and comparator vaccine groups.

No cases of myocarditis or pericarditis were reported within 42 days after vaccination in the mRNA-1010 group in the integrated analysis. The FDA nevertheless requires ongoing postmarketing monitoring for myocarditis, pericarditis, Guillain-Barré syndrome, and deaths, including unspecified-cause deaths. Continued surveillance is a normal and essential part of vaccine safety oversight.

Who Should Consider mFlusiva?

mFlusiva is FDA approved for adults age 50 and older. The best flu-vaccine choice depends on age, health conditions, prior vaccine reactions, local availability, and personal preferences.

  • Adults age 50 to 64 may discuss mFlusiva as a newly approved flu-vaccine option.
  • Adults age 65 and older should discuss mFlusiva alongside other enhanced flu-vaccine options, including high-dose, adjuvanted, and recombinant formulations.
  • People with a history of severe allergic reaction to a vaccine component should seek individualized guidance before vaccination.
  • People who are moderately or severely ill should generally wait until recovery before receiving routine vaccination.
For older adults: Flu vaccination is only one part of respiratory-disease prevention. Ask your healthcare professional whether you are up to date on RSV, pneumococcal, and COVID-19 vaccines based on current CDC guidance and your personal health history.

Frequently Asked Questions

Is mFlusiva the first mRNA flu vaccine approved in the United States?

Yes. Moderna’s mFlusiva is the first FDA-approved mRNA vaccine specifically for seasonal influenza in the United States.

Does mFlusiva replace every other flu shot?

No. Other influenza vaccines remain important options. The right product depends on age, medical history, vaccine availability, and current public-health recommendations.

Is the 26.6% result an absolute reduction in flu risk?

No. It is relative vaccine efficacy versus a standard-dose flu vaccine. In the trial, PCR-confirmed influenza-like illness occurred in 2.0% of mFlusiva recipients and 2.8% of comparator recipients.

Does mFlusiva contain live virus?

No. The vaccine contains mRNA instructions packaged in lipid nanoparticles. It does not contain live influenza virus and cannot cause influenza infection.

Can I receive mFlusiva with other vaccines?

Talk with your healthcare professional. The FDA review noted that data on coadministration with COVID-19, RSV, and pneumococcal vaccines were limited at the time of approval.

Bottom Line

Moderna’s mFlusiva marks an important advance: it is the first FDA-approved mRNA flu vaccine for adults 50 and older, and it outperformed a standard-dose influenza vaccine in a large clinical trial. The technology may improve manufacturing speed and reduce limitations associated with egg-based vaccine production.

At the same time, clear communication matters. The strongest clinical-efficacy evidence is versus a standard-dose flu vaccine. For adults 65 and older, high-dose comparator data are currently based on immune response, and a confirmatory study is still required to establish clinical benefit. The available data support a favorable benefit-risk profile, with the usual expectation of ongoing safety monitoring and transparent reporting.

Sources and Further Reading

  1. U.S. Food and Drug Administration. Clinical Review: mFlusiva (mRNA-1010), August 5, 2026.
  2. U.S. Food and Drug Administration. Vaccines and Related Biological Products Advisory Committee Briefing Document: mRNA-1010.
  3. Centers for Disease Control and Prevention. Influenza Vaccination Information.
  4. KundlasMD. FDA Approves Moderna’s mRNA Flu Shot for Adults 50+: Video Explanation.

About Dr. Kulmeet Kundlas

Dr. Kulmeet Kundlas is a physician and healthcare educator who creates practical, evidence-based content on preventive care, vaccines, chronic disease management, and medical innovation. His goal is to help patients make informed healthcare decisions using clear, balanced medical information.

Watch the Full Video

Learn more about Moderna’s mRNA flu vaccine, vaccine safety, and preventive care from Dr. Kulmeet Kundlas.

Subscribe to KundlasMD on YouTube


When your upper back feels stiff, even simple stuff—like reaching for something, turning while driving, or just sitting comfortably—gets trickier than it should. You’ll notice it most when you work out, but even daily tasks feel tougher. A bit of tightness in your thoracic spine can throw everything else out of whack because your lower back and neck start picking up the slack.

The fix? Thoracic mobility exercises.

Your thoracic spine is that middle section between your neck and low back. It’s responsible for a lot: twisting, bending, extending, and, honestly, most of your upper body’s big movements. When it’s not moving well, other areas try to help out—and that usually leads to more problems.

The best part: You don’t need special equipment, fancy routines, or a gym membership. With a handful of practical exercises, you can start moving that upper back with ease.

What Does Thoracic Mobility Mean?

Your thoracic spine sits right in the middle of your back, locked in by your rib cage. It has 12 vertebrae (T1-T12), and while it doesn’t bend and twist as much as your neck or lower back, it’s still important for all kinds of movement. Think of it like an anchor that lets you reach, rotate, bend to the side, or open up your chest for a big breath.

The goal isn’t crazy flexibility. You just want enough range of motion to move comfortably through daily life without your body constantly making up for lost motion somewhere else. For most people, it’s extension (arching back) and rotation (twisting) that get restricted first.

What’s Thoracic Extension?

Every time you go from a rounded, slouchy position to sitting tall or lifting your chest, that’s thoracic extension. You use it to reach overhead, throw a ball, lift weights, swim, or even reach for a mug in the cupboard.

One common issue: Your lower back tries to take over. When you practice thoracic extension, focus on arching through your upper and middle back—not your low back or ribs popping out. It’s better to move slowly and with control.

Why Is Your Upper Back So Stiff?

Let’s be honest: Most of us spend way too much time sitting. We drive, work at computers, watch TV…you get the idea. Your body adapts to whatever you do most, so long hours in one position lead to stiffness.

But it’s not just sitting. Limited shoulder movement, tight chest or back muscles, rib or spine injuries, age, and even just moving the “wrong way” for too long—it all adds up.

And stretching alone isn’t magic. Sometimes you actually have enough range, but you haven’t trained your body to use it well. That’s why you need mobility work that combines both stretching and controlled movement.

The 10 Best Thoracic Mobility Exercises

No need to do all ten in one go. Pick a few that address the motions that feel tight and stick with them. If something hurts or feels worse, skip it.

1. Cat-Cow

Start on hands and knees. Hands under your shoulders, knees under your hips. Round your back up toward the ceiling (cat), then gently lower your chest and look up (cow). Move slow—8 to 12 reps. Focus on smooth motion in your whole spine.

2. Quadruped Thoracic Rotation

Stay on hands and knees. Put your right hand behind your head. Keep your hips squared. Bring your right elbow toward your left arm, then rotate open (elbow points up). Go slow—6 to 10 reps each side. The goal is rotating through your upper back, not your hips.

3. Thread the Needle

Still on hands and knees, lift your right hand and reach it under your left arm, twisting through your upper back. Pause, then reverse. Repeat 6 to 8 times per side. Keep your breath relaxed.

4. Side-Lying Open Book

Lie on one side with knees bent and stacked. Reach both arms straight in front of you. Move your top arm across your chest, letting your chest rotate open. Pause, then bring it back. 6 to 10 reps per side. Don’t force your hand to the floor—just rotate as far as feels comfortable.

5. Side-Lying Thoracic Windmill

Similar setup as open book. Sweep your top arm in a big circle around your head, letting your chest and upper back twist naturally. 5 to 8 slow circles per side. Stay relaxed.

6. Chair Thoracic Extension

Sit on a sturdy chair, feet on the floor. Place your hands behind your head and lean your upper back over the chair back. Keep your core gently braced—don’t over-arch your low back. 6 to 10 reps.

7. Foam Roller Thoracic Extension

Sit on the floor, foam roller under your upper back. Support your head with your hands. Gently extend your upper back over the roller. Pause, return. Repeat 5 to 8 times. You can shift the roller up or down a bit to hit different spots. Don’t roll over your neck or low back.

8. Bench Thoracic Extension

Kneel in front of a bench or chair. Place your elbows on it. Shift your hips back and gently lower your chest, letting your upper back extend. Pause at a stretch, then return. 5 to 8 reps or hold for 10–20 seconds.

9. Standing Thoracic Extension Stretch

Facing a wall or desk, put your hands on the surface. Walk your feet back, push your hips behind you, and lower your chest between your arms. Keep it comfortable. Hold for 15–30 seconds or do 5 slow reps.

10. Seated Thoracic Rotation

Sit near the edge of a chair, feet flat. Cross your arms over your chest. Rotate your upper body to one side, then the other—keeping your hips and knees still. 6 to 10 reps per side.


Thoracic Mobility Without Equipment

Honestly, most of the best thoracic mobility drills don’t need gear. Cat-cow, quadruped rotations, thread the needle, open books, windmills, seated rotations—all you need is a bit of floor space and a chair. Fancy tools are nice, but just showing up and moving wins the day. Five to ten minutes a few times a week will beat one long session every now and then, every time.

Man performing an upper back mobility stretch at home

A Simple Thoracic Mobility Routine

Want to keep it simple? Here’s a quick routine:

1. Cat-Cow — 8 reps
2. Quadruped Rotation — 6 each side
3. Side-Lying Open Book — 6 each side
4. Chair or Foam Roller Extension — 6 to 8 reps
5. Standing Thoracic Extension — 5 reps, breathe normally

You can finish this in under 10 minutes—whether you’re starting your day, taking a break from your desk, or warming up for a workout.

Common Mistakes to Watch Out For

  1. Arching your lower back: During extension drills, keep a light brace in your core. If your ribs pop forward, dial it back—focus on your upper back.
  2. Hips moving during rotation: Try to keep your pelvis still so the twist really comes from your thoracic spine.
  3. Forcing the stretch: Stiff doesn’t mean your body needs to be yanked into a new position. Stay comfortable—sharp pain isn’t progress.
  4. Going too fast: Fast reps usually mean your body cheats the movement. Slow down so you notice where movement really comes from.
  5. Only stretching: Real mobility means controlling the movement, not just passively hanging out at your end range.

How Often Should You Do These Exercises?

There’s no one-size-fits-all answer. If your upper back’s pretty stiff, quick daily sessions—3 to 10 minutes—work best. Try adding them during breaks, before you work out, or as a little wind-down in the evening. Listen to your body; pain that gets worse is a sign to back off and maybe check in with a pro.

Mobility vs. Flexibility

Flexibility is about how far a muscle or tissue can stretch. Mobility is about how well you can control that range. You can be flexible when lying on the floor, but struggle to use that range standing or lifting. So don’t just “stretch farther”—instead, explore, control, and actually use the new mobility you’re building.

When Should You See a Physical Therapist?

Some tightness is just normal life. But see a professional if you have:

  • Severe or worsening pain
  • Pain after an injury or accident
  • Weakness, numbness, or tingling in your limbs
  • Pain wrapping around your ribs
  • Trouble with balance or walking
  • Known spine diagnoses, or symptoms that simply aren’t improving

Sometimes what you think is “just stiff” needs hands-on assessment—not more at-home stretching.

FAQ

Q. What are the best thoracic mobility exercises?
Cat-cow, quadruped rotations, open books, thread the needle, chair or foam roller extensions, and seated rotations make a great starter list. Pick based on what feels tight—extension, rotation, or both.

Q. How do you stretch the thoracic spine?
Start with gentle motions—cat-cow, open book, seated rotation, chair extension. Don’t yank into the biggest stretch; just move to a comfortable range.

Q. Best thoracic extension exercises?
Try chair extension, foam roller extension, bench extension, or standing extension—aim for upper back movement, not over-arching your low back.

Q. Best thoracic rotation exercises?
Open book, thread the needle, quadruped rotations, seated rotations, and thoracic windmills all help.

Q. Can you get results without equipment?
Absolutely. Most effective thoracic mobility work just needs your body and a little space.

Q. Can you do these every day?
Gentle, comfortable exercises are fine to do most days if you’re not feeling any pain or new issues. No need to force your max range every session.

Q. How long until you notice improvement?
It depends. Consistency matters more than how hard you stretch. Over time, daily movement—reaching, rotating, lifting—should start feeling smoother.

Final Thoughts

Thoracic mobility doesn’t have to be complicated. Start with simple moves like cat-cow, open book, quadruped rotations, chair extension, or foam roller extension. Pick a few, do them regularly, and don’t worry about finding the “perfect” drill. The big thing is moving consistently—slow, relaxed, and with control. Forget chasing extreme flexibility; the goal is a comfortable, mobile upper back that supports your daily movement and workouts.

Scroll to Top